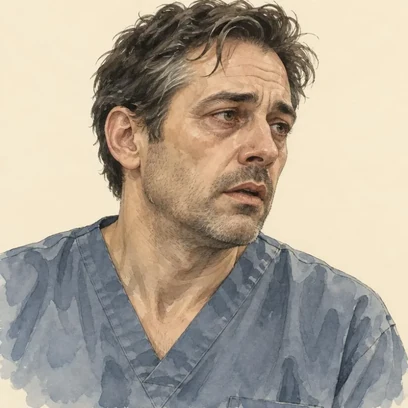
Acidotic Andy
Metabolic Acidosis
Written lecture — video coming
The memory hook
Kussmaul breathing, fruity breath, pH ↓ · HCO₃⁻ ↓
The story
Andy pulls into the DKA Diner running on empty, orders a fruity milkshake and starts breathing like a steam engine. Every deep breath is his lungs trying to blow the acid out of a body that has already run out of insulin.
Andy is a brilliant but chronically overloaded mechanical engineering student who treats his Type 1 diabetes like an optional maintenance schedule. Known around campus as Acidotic Andy, he earned the nickname not just for his sour, irritable demeanor during exams, but because his body is perpetually teetering on the edge of severe metabolic decompensation. In metabolic acidosis, excess hydrogen ions flood the vascular space while bicarbonate is consumed, causing the systemic pH to plummet. When Andy ignores his body, glucose remains locked outside his cells, starving them of fuel. In response, his liver furiously metabolizes fatty acids, releasing an avalanche of acetoacetic and beta-hydroxybutyric acids that systematically overwhelm his blood's natural chemical buffers.
The crisis begins quietly during finals week when Andy pulls consecutive all-nighters, substituting regular sugary sodas for meals and missing two full days of basal insulin. Without circulating insulin, glucose piles up in his bloodstream, creating hyperosmolar serum and triggering severe osmotic diuresis. He urinates incessantly, losing vital water and electrolytes while believing he is just dehydrated from excess caffeine. Early warning signs creep in: deep muscular weakness, generalized abdominal cramping, nausea, and relentless thirst. His skin turns warm and flushed due to peripheral vasodilation caused by mounting acidemia. As his cells starve amidst plenty, his body burns adipose tissue at a furious pace, pouring acidic ketone bodies into the circulation and tipping him into uncompensated high anion gap metabolic acidosis.
By morning, Andy’s roommate discovers him slumped at his desk, obtunded and panting with loud, deep, tireless Kussmaul respirations. A distinct, sickly sweet odor of acetone wafts across the room like nail polish remover, signaling exhaled ketones. In the emergency department triage bay, Andy is severely lethargic, responding only to noxious stimuli. His arterial blood gas reveals a critical uncompensated metabolic acidosis with partial respiratory compensation: arterial pH is 7.12, serum bicarbonate drops to a dismal 8 mEq/L, and his PaCO2 is 24 mmHg as his hyperventilating lungs desperately blow off carbon dioxide. His serum anion gap spikes dangerously to 22 mEq/L. Serum potassium reads 5.8 mEq/L because acidosis shifts hydrogen into cells and forces potassium into the bloodstream.
The primary nurse moves rapidly through clinical priorities, recognizing that treating the underlying cause requires careful sequencing. The first action is initiating rapid intravenous fluid resuscitation with normal saline to restore circulating intravascular volume and renal perfusion. Before touching the regular insulin infusion, the nurse confirms the initial serum potassium level is above 3.3 mEq/L, preventing sudden lethal hypokalemia as insulin drives potassium back intracellularly. Once cleared, an intravenous regular insulin drip is initiated with continuous cardiac telemetry monitoring for peaked T-waves or lethal dysrhythmias. The nurse meticulously charts hourly neuro checks and urine output, guarding against cerebral edema from overly rapid osmolality shifts. Reflexive administration of intravenous sodium bicarbonate is strictly withheld, as rapid alkalization can precipitate severe rebound hypokalemia and paradoxical central nervous system acidosis.
The setup
Andy skips two days of insulin during finals week and lives on soda. Cells starve while sugar piles up in the blood outside them.
The turn
By morning he is breathing like a steam engine — deep, tireless, loud — and his roommate smells nail polish on his breath.
The crisis
In triage his pH reads 7.12, his anion gap is 22, and his potassium comes back high even though he has been urinating out potassium for two days.
The save
The nurse hangs isotonic fluids, checks potassium before touching the insulin drip, then titrates and rechecks — no bicarb hero moves.
Already a member? Sign in