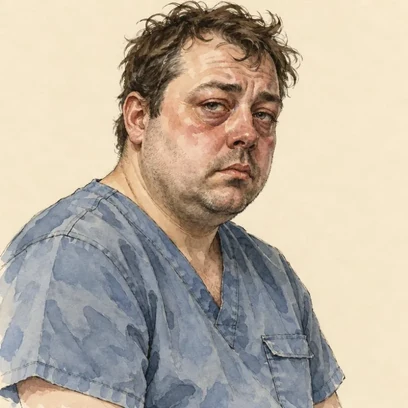
Anuric Alan
Acute Kidney Injury
Written lecture — video coming
The memory hook
Urine < 30 mL/hr, K⁺ ↑, creatinine ↑ — find the cause first
The story
Alan had a CT with contrast on Monday and takes ibuprofen most days. By Wednesday his ankles are swollen, he is short of breath, and the collection container by the bed is nearly empty.
Alan is a dependable warehouse dispatcher who prides himself on keeping the supply chain moving without taking breaks or complaining about his chronic joint pain. He earned the clinical nickname Anuric Alan because his nephrons have abruptly shuttered their filtering stations, grinding urine production to a sudden and dangerous halt. In acute kidney injury, the renal parenchyma suffers an abrupt decline in glomerular filtration rate, resulting in the rapid accumulation of nitrogenous waste products and electrolytes. Prerenal insults deprive the organ of perfusion, intrarenal damage attacks the cellular architecture itself, and postrenal blockages choke the outbound flow. Alan personifies the severe intrarenal crisis, where nephrons lose their concentrating capacity, leaving fluid trapped inside the intravascular space and transforming a once-reliable excretory system into a stalled, toxic reservoir.
The cascade began three days ago after Alan underwent an outpatient computed tomography scan with intravenous iodinated contrast dye to investigate persistent abdominal pain. To power through lingering discomfort, he consumed high doses of over-the-counter ibuprofen every six hours, entirely unaware that nonsteroidal anti-inflammatory drugs constrict afferent arterioles and cripple renal hemodynamics. A sudden gastrointestinal bug struck the next night, and repeated vomiting left him severely volume depleted, layering prerenal hypoperfusion directly on top of chemical intrarenal toxicity. His urine output quietly plummeted below thirty milliliters per hour, dropping to barely twenty milliliters per hour by Wednesday morning. His serum creatinine surged upward by more than zero point three milligrams per deciliter within forty-eight hours, doubling from his baseline alongside a climbing blood urea nitrogen.
By Wednesday afternoon, Alan arrived at the emergency department gasping for air, lethargic, and disoriented from circulating uremic toxins. His ankles displayed four-plus pitting edema, coarse crackles echoed across both lung bases, and his jugular veins were visibly distended, reflecting a sudden four-kilogram weight gain over forty-eight hours. The bedside cardiac monitor immediately alarmed, displaying ominous, tall peaked T waves driven by a serum potassium of six point three milliequivalents per liter. Laboratory results revealed a serum creatinine of three point four milligrams per deciliter, a blood urea nitrogen of sixty-eight milligrams per deciliter, and arterial blood gas analysis indicating metabolic acidosis. His urine specific gravity was fixed at one point zero one zero, confirming tubular necrosis, while his collection container held barely ten milliliters of dark, amber fluid.
The nurse acted swiftly, recognizing that hyperkalemia and acute pulmonary edema threatened Alan's life far more urgently than his creatinine. The nurse immediately halted all nephrotoxic medications, strictly forbidding further nonsteroidal anti-inflammatory drugs, contrast agents, and aminoglycosides. The team administered intravenous calcium gluconate to stabilize the cardiac membrane, followed by regular insulin given intravenously with fifty percent dextrose to drive potassium back into cells. Sodium polystyrene sulfonate was administered orally to bind and eliminate potassium through the digestive tract. The nurse placed an indwelling catheter for strict hourly urine measurement, instituted severe dietary restrictions on fluid, sodium, and potassium, and prepared the patient for emergent hemodialysis. Hourly pulmonary assessments and daily weights performed on the identical scale at the same time were initiated to guide fluid removal.
The setup
Contrast dye, daily NSAIDs and a bout of vomiting that left him dry — three insults to the same kidney.
The turn
Urine output falls to 20 mL/hr, creatinine doubles in 48 hours and BUN climbs with it.
The crisis
Potassium is 6.3 with peaked T waves, crackles fill both bases, and his weight is up 4 kg in two days.
The save
Nephrotoxins are stopped, fluids and potassium are restricted, insulin with dextrose shifts potassium in while sodium polystyrene removes it, and daily weights track the fluid.
Already a member? Sign in