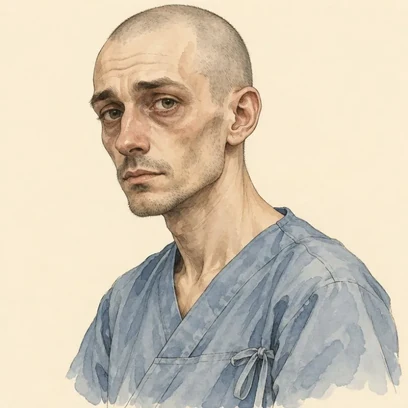
Lysing Luis
Tumor Lysis Syndrome
Written lecture — video coming
The memory hook
K⁺ ↑, uric acid ↑, phosphate ↑, Ca²⁺ ↓ — cells burst 24–72 hrs post-chemo
The story
Luis feels fine right after his infusion, proud he tolerated it so well. Thirty-six hours later he is cramping, his urine has slowed, and the monitor shows peaked T waves.
Luis is a competitive glassblower known for pushing delicate, superheated vessels to their absolute physical limits. Just like fragile glass that shatters under sudden pressure in his workshop, his body hosts a massive, rapidly dividing lymphoma primed for catastrophic destruction. His clinical moniker, Lysing Luis, reflects the violent cellular rupture occurring at a microscopic level within his lymphatic system. When tumor cells burst open under stress, they flood the bloodstream with their intracellular contents, completely overwhelming normal renal and metabolic clearance. Luis is naturally jovial, determined, and eager to obliterate his malignancy, unaware that the rapid death of millions of malignant cells can be as lethal as their growth. His internal equilibrium teeters precariously as his fragile cellular membranes prepare to disintegrate simultaneously.
The crisis began shortly after Luis completed his very first aggressive chemotherapy infusion for his bulky lymphoma. Highly chemosensitive hematologic malignancies carry the greatest threat, acting like an overpacked warehouse waiting to collapse under pressure. Throughout the initial twenty-four hours, Luis felt deceptively well, even boasting to his oncology nurse that he had sidestepped the anticipated nausea and fatigue. However, beneath this calm surface, toxic cellular debris was relentlessly accumulating. Intracellular nucleic acids were rapidly metabolizing into insoluble uric acid, while intracellular phosphate and potassium were surging into systemic circulation. By thirty-six hours post-chemo, subtle warning signs crept in. Luis experienced mild nausea, generalized muscle weakness, and noticed his urine was darkening to an amber tint while diminishing in total volume, signaling impending renal tubule obstruction.
By hour forty-eight, Luis plunged into a full clinical emergency. He awoke with severe involuntary muscle cramps in his calves and a persistent, distressing tingling sensation around his mouth. He complained of dull flank pain, and his urine output plummeted to an alarming twenty milliliters over four hours. On telemetry, his previously normal cardiac rhythm warped into dangerous, tall, peaked T waves. Urgent stat blood work confirmed classic tumor lysis syndrome. His serum potassium surged dangerously to 6.4 mEq/L, his phosphate escalated to 8.9 mg/dL, and his uric acid spiked to 11.2 mg/dL. In response to the immense phosphate surge, ionized calcium bound tightly to form insoluble precipitates, plunging his serum calcium to a critical 6.8 mg/dL and triggering severe neuromuscular irritability.
The nurse recognized the oncologic catastrophe instantly and executed priority interventions without hesitation. First, aggressive intravenous hydration with normal saline was initiated at two hundred milliliters per hour to flush the renal tubules and maintain brisk urine output. The nurse immediately administered intravenous rasburicase to enzymatically break down circulating uric acid into soluble allantoin, while simultaneously initiating cardiac protocols to lower potassium and protect the myocardium. Continuous cardiac telemetry monitored every beat, while the nurse instituted strict intake and output tracking with hourly urine checks. The nurse strictly avoided any intravenous fluids or supplements containing potassium or phosphate, as supplemental electrolytes could trigger fatal dysrhythmias. Frequent serum chemistries and renal panels were scheduled every four hours to ensure toxic cellular debris cleared safely.
The setup
Luis has a large, fast-growing lymphoma — exactly the kind of tumor that lyses rapidly once chemotherapy starts.
The turn
He feels well the day of treatment, so no one is alarmed — but his labs already show uric acid climbing.
The crisis
He develops muscle cramps and tingling around his mouth, his urine output drops, and the monitor shows peaked T waves. Potassium is 6.4, phosphate is 8.9, calcium is 6.8.
The save
Aggressive IV fluids flush the kidneys, rasburicase breaks down uric acid, potassium is treated per protocol, and cardiac monitoring continues until labs normalize.
Already a member? Sign in