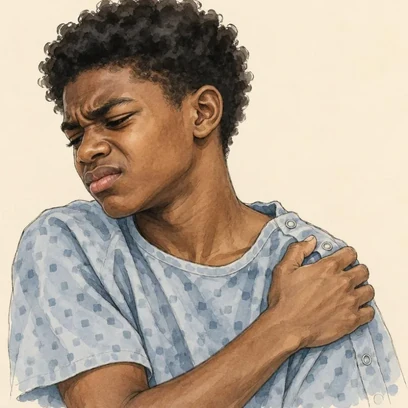
Sickled Simon
Sickle Cell Vaso-Occlusive Crisis
Written lecture — video coming
The memory hook
Severe bone pain, dactylitis, priapism risk — hydrate, oxygenate, treat pain around the clock
The story
Simon, age 7, wakes screaming with pain in his legs and back after playing outside in cold weather without a jacket. He has had sickle cell disease since infancy and knows this pain well.
Simon is an energetic seven-year-old boy who loves soccer and building intricate plastic model airplanes in his sunny bedroom. Diagnosed with homozygous sickle cell anemia in infancy, his name Sickled Simon perfectly captures the microscopic war raging inside his circulation. Normally round, flexible erythrocytes contort into rigid, crescent-shaped sickles whenever physiologic stress strikes. These stiff cells lose their pliability, clustering together like jagged logs jamming a narrow stream. Instead of gliding effortlessly through capillaries, the clumped red cells obstruct microvascular blood flow throughout his skeletal system. This vaso-occlusion robs tissues of vital oxygen, causing excruciating ischemia, tissue infarction, and intense inflammation. Simon understands that while his spirit remains boundless, his fragile red blood cells are constantly balanced on the edge of a painful vascular blockade.
The crisis begins on a brisk, overcast autumn afternoon when Simon loses track of time playing kickball without wearing his heavy winter coat. Exposed to piercing winds and ignoring his dry mouth, the combined insults of cold exposure and progressive dehydration rapidly tip his delicate vascular equilibrium. In sickle cell disease, cold causes peripheral vasoconstriction while dehydration concentrates the blood, creating a lethal combination that promotes hemoglobin S polymerisation. By the time Simon trudges home shivering, early warning signs emerge as a dull, heavy ache across his lumbar spine and both femurs. His mother remembers his toddler years marked by painful dactylitis and notes his growing lethargy, marked conjunctival pallor, and mild scleral icterus. Despite drinking a glass of water and taking oral ibuprofen, Simon’s aching joints steadily intensify into an unrelenting, throbbing torment.
By midnight, Simon arrives at the emergency department screaming in agony, rating his bilateral leg pain as an unbearable eight out of ten and refusing to bear weight. The crisis takes an alarming turn when he suddenly develops sharp anterior chest pain, a dry persistent cough, and marked tachypnea with a respiratory rate of thirty-two breaths per minute. His oxygen saturation dips to eighty-nine percent on ambient air, and a low-grade fever of 101.4 degrees Fahrenheit triggers fears of acute chest syndrome and overwhelming encapsulated bacterial sepsis. Venous blood draw confirms profound anemia with a hemoglobin level plummeting to 6.8 grams per deciliter, down from his typical baseline of 8.0 grams per deciliter. His reticulocyte count is markedly elevated at eleven percent, reflecting hyperactive erythropoiesis, alongside a leukocytosis of 18,500 white blood cells per microliter.
The pediatric nurse acts swiftly, recognizing that rapid, systematic intervention halts the vicious cycle of sickling and tissue necrosis. The nurse immediately applies supplemental oxygen via nasal cannula to correct his hypoxia, and starts aggressive intravenous rehydration with hypotonic dextrose fluids at one-and-a-half times maintenance to decrease serum osmolarity and unclog microvessels. To master his severe agony, the nurse administers scheduled intravenous morphine around the clock rather than relying on delayed PRN dosing, ensuring constant therapeutic blood levels. The nurse applies soothing warm blankets to his aching extremities to promote vasodilation, strictly avoiding ice packs or cold compresses, which cause severe peripheral vasoconstriction and exacerbate microvascular sickling. Continuous pulse oximetry, serial respiratory assessments, and urgent notification of the pediatric hospitalist ensure that Simon's acute chest syndrome receives prompt, life-saving therapeutic escalation.
The setup
Simon plays outside on a cold, windy day and comes home dehydrated and shivering, then complains his legs ache.
The turn
By evening the ache has become throbbing pain in his long bones, and he rates it 8 out of 10, refusing to walk.
The crisis
In the ED his pain is unrelenting despite one dose of ibuprofen, his respiratory rate climbs, and he develops chest pain with a mild cough.
The save
The nurse starts IV fluids, administers scheduled IV opioids around the clock rather than waiting for pain to peak, applies supplemental oxygen, and notifies the provider immediately about his chest symptoms.
Already a member? Sign in