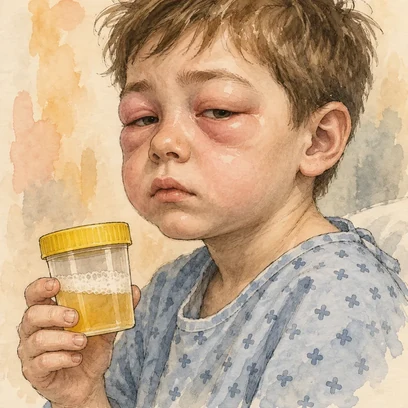
Nephrotic Nolan
Childhood Nephrotic Syndrome: Puffy Eyes, Frothy Urine & Protein Loss
Written lecture — video coming
The memory hook
His eyelids are swollen shut in the morning and his urine foams — protein is leaking straight out of him
The story
Nolan's mother thought his eyes were puffy from crying. Four days later his belly is swollen, his urine foams, and he has gained six pounds.
Nolan's parents gave him his nickname after noticing his eyes were puffy every single morning, so swollen some days that he could barely peek through his lashes until well after breakfast. That puffiness was the hallmark of childhood nephrotic syndrome, a condition in which the glomerular filtration barrier in his kidneys becomes abnormally permeable to protein, allowing massive amounts of albumin to leak out into his urine. As his serum albumin plummets, the plasma oncotic pressure that normally keeps fluid inside his blood vessels weakens, so fluid shifts steadily into his tissues, producing the periorbital and generalized edema that gave him his name. His liver compensates for the protein loss by manufacturing excess lipoprotein, driving his cholesterol upward, while his lost immunoglobulins leave him unusually vulnerable to infection.
Nolan is brought to the pediatrician after his mother notices his school pants no longer fit around his suddenly swollen abdomen, and she mentions almost as an afterthought that his urine has started foaming dramatically in the toilet bowl, almost like dish soap. A urine dipstick in the office reveals protein at 4+, and his serum albumin returns critically low at 1.8 g/dL, confirming the diagnosis of nephrotic syndrome. Notably, his blood pressure remains entirely normal, an important detail that helps the pediatric nephrologist distinguish this presentation clearly from glomerulonephritis, which instead typically features hematuria alongside hypertension. Nolan is started on corticosteroid therapy and admitted briefly for close monitoring of his rapidly accumulating fluid.
Over the next three days, Nolan's daily weight climbs from 22 kg to 24.3 kg, representing roughly 2.3 liters of retained fluid pooling silently in his tissues and abdomen. His abdominal girth measurement grows by nearly four centimeters, and his cholesterol returns markedly elevated at 310 mg/dL. On his second day of steroid therapy, his temperature spikes suddenly to 101.5°F, and he begins complaining of diffuse abdominal pain, findings his nurse recognizes immediately as concerning for peritonitis, a dangerous infectious complication that nephrotic children are especially prone to given their urinary loss of protective immunoglobulins combined with immunosuppressive steroid therapy.
Nolan's nurse obtains his weight at the same time every single morning using the same scale, tracking this trend as the single most reliable indicator of his fluid status, alongside daily abdominal girth measurements and urine protein checks. She administers his prednisone exactly as prescribed, never stopping it abruptly even as his appetite noticeably increases and his face rounds with the medication's expected effects, and she reports the new fever and abdominal pain to the provider immediately given the concern for peritonitis. She protects Nolan proactively from infection by limiting visitors with any signs of illness and reinforcing careful hand hygiene for everyone entering his room, understanding that his immunosuppressed, protein-depleted state leaves him with very little reserve to fight off even minor infections.
The setup
Nolan's eyelids are puffy each morning and improve a little by afternoon, so the swelling is dismissed as allergies.
The turn
His abdomen distends, his urine foams in the toilet, and he gains six pounds in a week.
The crisis
Nolan spikes a fever, and the nurse knows an infection in this child is dangerous.
The save
Nolan starts corticosteroids, is weighed daily on the same scale with abdominal girth measured, eats a low-sodium diet, and his fragile swollen skin is protected and repositioned.
Already a member? Sign in