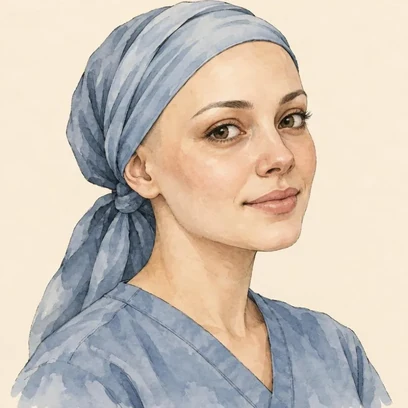
Neutropenic Nia
Neutropenia & Chemotherapy Precautions
Written lecture — video coming
The memory hook
ANC < 500, temp ≥ 100.4°F — a single fever is an emergency
The story
Nia feels 'just tired' the week after her infusion and almost skips her temperature check. The thermometer reads 100.6°F, and everything moves fast after that.
Nia is a passionate botanical illustrator whose studio usually bursts with fragrant cuttings, damp potting soil, and vibrant orchids. Known among her friends for her meticulous precision and boundless energy, she approaches life with radiant optimism, even after being diagnosed with cancer and starting aggressive systemic therapy. Her mnemonic moniker, Neutropenic Nia, directly reflects the profound cellular fallout within her bone marrow. The cytotoxic medications designed to eradicate rapidly dividing malignant cells simultaneously decimate her rapidly dividing myeloid precursors. Her absolute neutrophil count, typically responsible for phagocytizing invading bacteria and orchestrating early inflammatory responses, has plummeted dramatically. Deprived of these frontline granulocyte defenders, Nia’s body is left entirely stripped of its primary cellular shields, rendering her vulnerable to opportunistic micro-organisms that a healthy immune system would effortlessly destroy.
Ten days prior, Nia completed her third intensive round of chemotherapy, placing her directly in the dreaded nadir window, which typically occurs seven to fourteen days post-infusion. During this nadir period, circulating blood cell counts strike their absolute lowest baseline. While Nia expected some standard exhaustion, she gradually developed subtle, non-specific symptoms that she almost dismissed as ordinary recovery fatigue. She felt washed out, unusually achy, and vaguely chilled, yet she had no productive cough, no dysuria, and no localized skin erythema. Because mature neutrophils are required to generate classic signs of inflammation such as swelling, redness, and purulent exudate, neutropenia effectively masks severe infections. Nia assumed she was simply experiencing post-treatment weariness, unaware that insidious bacterial colonization was already advancing quietly without standard physical warning signs.
On the morning of day ten, Nia felt a wave of shivering and reluctantly reached for her digital oral thermometer. The display flashed 100.6°F, exceeding the critical febrile threshold of 100.4°F, or 38°C. Recognizing the urgent instructions from her oncology team, she reported to the emergency triage center immediately. Her morning complete blood count with differential revealed an absolute neutrophil count of only 380/mm³, far below the normal range of 2,500 to 6,000/mm³ and meeting the diagnostic criteria for severe neutropenia beneath 500/mm³. Her vital signs demonstrated a compensatory heart rate of 118 beats per minute and a blood pressure of 96/60 mm Hg. Physical assessment showed pale, dry oral mucosa with mild stomatitis but entirely lacked purulent drainage, illustrating how febrile neutropenia presents as an isolated, life-threatening fever.
The nurse recognized a septic emergency, instantly alerting the provider and executing neutropenic protocols without hesitation. Priority one was obtaining two sets of blood cultures from separate venipuncture sites before hung therapy commenced. Within forty-five minutes of presentation, well inside the mandatory one-hour window, the nurse initiated broad-spectrum intravenous piperacillin-tazobactam, refusing to wait for preliminary lab culture growth. Nia was promptly transferred to a private room where strict protective precautions were enacted, requiring meticulous hand hygiene for all personnel, dedicated equipment, and the removal of standing water, fresh flowers, and unpeeled raw produce. To prevent mucosal trauma and opportunistic bacteremia, the nurse strictly prohibited rectal temperature monitoring, suppositories, enemas, and intramuscular injections, continuously reassessing Nia’s blood pressure and mentation for progression into septic shock.
The setup
Chemotherapy knocks down every fast-dividing cell in Nia's body, including the neutrophils in her bone marrow.
The turn
She feels washed out and achy but has no cough, no burning with urination, nothing obvious to point to.
The crisis
Her temperature reads 100.6°F. Her ANC from this morning's labs is 380/mm³.
The save
The nurse calls the provider immediately, blood cultures are drawn from two sites, and broad-spectrum IV antibiotics are hung within the hour — before the culture results are even back.
Already a member? Sign in