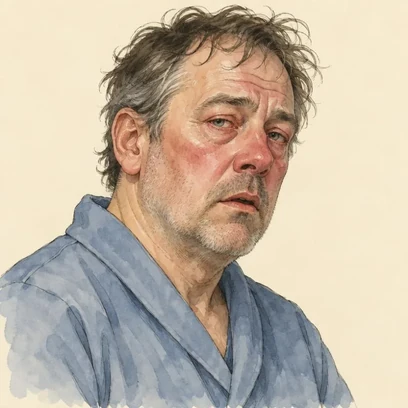
Septic Sam
Distributive Shock
Written lecture — video coming
The memory hook
Warm flushed skin early, then BP bottoms out
The story
Sam throws a party in every blood vessel he owns — everything dilates, everything opens up. For an hour he's warm and pink and looks fine. Then the party drains the tank and his pressure falls through the floor.
Samuel Septic Sam Vance is a retired neighborhood block-party coordinator known for throwing open every door and inviting everyone inside. That hospitable nature mirrors his vascular bed when distributive shock sets in, turning his circulatory system into one giant, uncontrolled gathering. Instead of maintaining normal systemic vascular resistance, Sams endotoxins trigger massive nitric oxide release and widespread vasodilation. Every peripheral vessel relaxes and opens wide, distributing his circulating blood volume into dilated capillary beds where it pools uselessly. To the untrained eye, Sam looks remarkably well at first because this vasodilation produces the hyperdynamic, warm phase of septic shock. His blood pools near the surface, painting him rosy pink while starving his vital organs of effective perfusion pressure deep within his core.
At seventy-eight years old, Sams trouble began quietly seven days ago with a common, untreated urinary tract infection. Older adults rarely mount an obvious, localized alarm, so Sam never complained of dysuria or flank pain; instead, his family simply noticed uncharacteristic, insidious confusion. He misplaced his keys, repeated stories, and spent mornings napping in his armchair. This subtle change in mentation was the initial warning sign of severe systemic infection spreading beyond his bladder. As uropathogens invaded his bloodstream, cytokines triggered systemic inflammatory cascades across his vascular endothelium. Capillaries became hyperpermeable, allowing intravascular fluid to leak into the third space. By the time his daughter noticed his disorientation and brought him to the emergency department, Sam was sliding from localized sepsis into the deceptive, early stages of distributive shock.
Upon arrival, Sam appeared deceptively robust with flushed, dry skin, bounding peripheral pulses, a heart rate of 118 beats per minute, and a temperature of 38.9 degrees Celsius. Yet this hyperdynamic warmth masked cellular suffocation. Within two hours, his compensatory mechanisms collapsed, and his mean arterial pressure plunged to 58 millimeters of mercury despite rapid crystalloid administration. Sams skin turned pale, cold, and mottled as distributive shock tipped into profound hypoperfusion. His serum lactate surged to 4.6 millimoles per liter, confirming severe anaerobic metabolism and tissue hypoxia. His white blood cell count spiked with a marked bandemia shift, while serum creatinine and blood urea nitrogen climbed as renal filtration failed. His urinary catheter drained zero urine, confirming acute kidney injury and anuria below 0.5 milliliters per kilogram per hour.
The nurse initiated the sepsis resuscitation protocol immediately, recognizing that rapid, structured intervention dictated survival. Priority one was drawing two sets of blood cultures from separate venipuncture sites before administering broad-spectrum intravenous piperacillin-tazobactam within the golden sixty-minute window. Delaying antibiotic administration or giving them before drawing blood cultures is strictly contraindicated, as premature antibiotics compromise pathogen identification. Concurrently, the nurse rapidly infused an isotonic crystalloid bolus at thirty milliliters per kilogram to fill Sams dilated vascular tank. When his mean arterial pressure lingered beneath sixty-five millimeters of mercury despite fluid completion, the nurse titrated intravenous norepinephrine through a central line as the first-line vasopressor. The team rechecked serum lactate every two hours and monitored continuous telemetry, Glasgow coma scores, and hourly urine output via an indwelling catheter.
The setup
A urinary tract infection in an 78-year-old goes untreated for a week; the only complaint is that he seems confused.
The turn
He arrives warm, pink and bounding — heart rate 118, temperature 38.9°C, blood pressure still 'okay.'
The crisis
Lactate is 4.6, MAP falls to 58 after two liters of fluid, and urine output stops.
The save
Cultures were drawn before the first antibiotic, 30 mL/kg of crystalloid went in, and norepinephrine is now titrated to a MAP of 65.
Already a member? Sign in