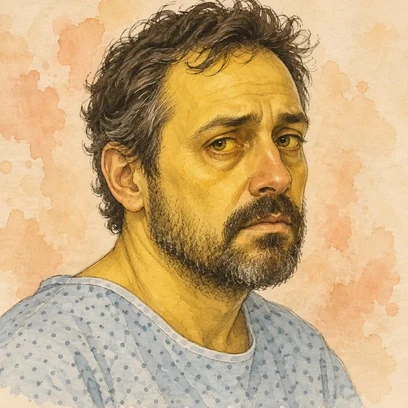
Hepatitis Hugo
Viral Hepatitis A, B & C
Written lecture — video coming
The memory hook
Jaundice, dark urine, clay stools and RUQ tenderness — know your route of transmission to know your teaching
The story
Hugo returned from a trip abroad two weeks ago and now feels exhausted, nauseated, and off his food. This morning his eyes look yellow in the mirror and his urine has turned the color of strong tea.
Hugo is an adventurous freelance travel photographer who has earned the nickname Hepatitis Hugo among his colleagues for his fearless habit of sampling street food from every roadside vendor he encounters during his international assignments. That daring nickname carries an unfortunate prophecy about his own liver health. Hepatitis viruses attack hepatocytes directly, triggering widespread inflammation that impairs the liver's essential ability to conjugate and excrete bilirubin properly. Depending on which viral strain invades his body, the consequences differ dramatically: hepatitis A spreads through the fecal-oral route via contaminated food or water and rarely becomes chronic, whereas hepatitis B and C transmit through blood and body fluids and frequently progress toward chronic liver disease, cirrhosis, or hepatocellular carcinoma over subsequent decades.
Hugo's current ordeal began after a three-week photography assignment through a region with limited sanitation infrastructure, where he enthusiastically sampled unwashed fruit and untreated well water from local street markets. Approximately three weeks after returning home, he began feeling unusually fatigued, losing his appetite entirely, and developing persistent low-grade nausea that made even simple meals unappealing. He initially attributed these symptoms to ordinary jet lag and travel exhaustion, continuing to edit photographs late into the night despite feeling progressively worse. A mild, intermittent fever accompanied his fatigue, though Hugo stubbornly delayed seeking medical evaluation for nearly another full week.
Everything changed one morning when Hugo glanced into his bathroom mirror and noticed his sclera had turned unmistakably yellow, while his urine had darkened to the color of strong steeped tea overnight. His most recent bowel movement appeared strikingly pale and clay-colored, and he developed noticeable tenderness beneath his right ribcage upon palpation. Emergency laboratory results revealed alarmingly elevated liver enzymes, with his ALT reaching 1,800 units per liter and AST climbing to 1,600 units per liter, alongside a total bilirubin level of 6.8 milligrams per deciliter. Positive hepatitis A IgM antibodies confirmed the diagnosis, and the medical team began closely monitoring Hugo for any signs of progression toward fulminant hepatic failure.
The nursing team prioritized promoting complete rest for Hugo to reduce metabolic demand on his severely inflamed liver, while encouraging a high-calorie, moderate-protein diet as tolerated to support hepatocyte regeneration without overburdening ammonia clearance. Acetaminophen and all other hepatotoxic substances were strictly avoided throughout his recovery period, and standard precautions with meticulous hand hygiene were reinforced given hepatitis A's fecal-oral transmissibility to close contacts. The nurse vigilantly monitored Hugo's mental status for early signs of hepatic encephalopathy, tracked his coagulation studies for any concerning prolongation, and provided thorough education about hepatitis A vaccination for his household members and travel companions moving forward.
The setup
Hugo ate street food while traveling and now, two to six weeks later, develops fatigue, low-grade fever, anorexia and nausea.
The turn
Hugo notices dark, tea-colored urine, pale clay-colored stools, and yellowing of his sclera, along with RUQ tenderness.
The crisis
Hugo's ALT rises to 1,800 units/L, AST to 1,600 units/L, and his total bilirubin climbs to 6.8 mg/dL, with worsening fatigue and pruritus.
The save
The nurse provides rest, a high-calorie/moderate-protein diet, monitors for bleeding and mental status changes, avoids hepatotoxic medications, and teaches strict hand hygiene and standard/contact precautions to prevent spread.
Already a member? Sign in