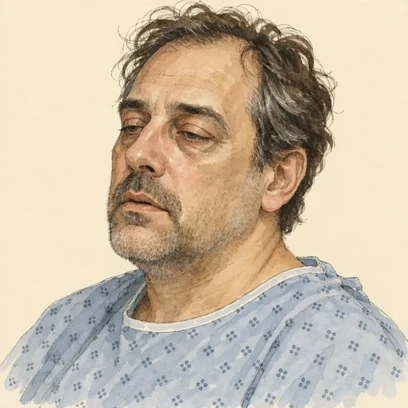
Vented Vince
Mechanical Ventilation
Written lecture — video coming
The memory hook
High-pressure alarm = obstruction; low = disconnection
The story
Vince cannot speak, so his ventilator does the talking. Learn its two alarms and you can hear exactly what is wrong with him from the doorway.
Vince used to be a charismatic auctioneer whose rapid-fire cadence mesmerized crowded halls, relying entirely on flawless breath control and booming vocal projection. Today, he lies in the intensive care unit as Vented Vince, stripped of his voice by a size eight oral endotracheal tube secured at twenty-three centimeters at the lip. The machine beside him dictates the rhythm of his life, delivering positive pressure breaths because his exhausted lungs can no longer sustain alveolar ventilation on their own. Vince embodies mechanical ventilation: a mechanical circuit replacing natural negative-pressure physiology. Because the plastic tube bypasses his vocal cords, Vince cannot speak, so every breath, pause, and clinical emergency is voiced instead by the rhythmic hum, rhythmic hiss, and startling electronic alarms of his life-sustaining ventilator.
His descent began a week earlier when a viral respiratory illness deteriorated into severe bilateral pneumonia and acute hypoxemic respiratory failure. Vince developed classic warning signs that signaled impending respiratory arrest: marked tachypnea, severe intercostal retractions, paradoxical abdominal breathing, and progressive diaphoresis. Despite receiving sixty percent oxygen via non-rebreather mask, his oxygenation plummeted, and his work of breathing became unsustainable. His arterial blood gas revealed severe respiratory acidosis with profound hypoxemia, forcing the rapid response team to initiate emergency endotracheal intubation. Once secured, clinicians confirmed proper tube depth via post-intubation chest radiography to prevent right-mainstem bronchus intubation. Vince was placed on continuous intravenous sedation with propofol to facilitate ventilator synchrony, but his fragile airway remained exceptionally vulnerable to dynamic changes in airway resistance and circuit integrity.
The crisis erupts when a piercing high-pressure alarm shrieks across the unit. Vince thrashes against the bed rails with ventilator dyssynchrony, biting down violently on the oral tube as coarse rhonchi rattle throughout his chest. His peak inspiratory pressure spikes beyond forty-five centimeters of water, his pulse oximetry drops precipitously to eighty-two percent, and end-tidal carbon dioxide surges to fifty-eight millimeters of mercury. An emergent arterial blood gas demonstrates acute respiratory acidosis: pH 7.22, PaCO2 62 mmHg, and PaO2 54 mmHg. Minutes after calming slightly, the room abruptly falls deathly silent as the ventilator sounds a frantic low-pressure alarm. Vince has no chest rise, his tidal volumes drop to zero milliliters, and his circuit lies completely disconnected at the wye adapter, threatening sudden asphyxiation, cardiovascular collapse, and immediate clinical arrest.
The critical care nurse executes the priority save by assessing Vince immediately rather than silencing the alarm console. Spotting the disconnected wye, the nurse instantly reconnects the circuit; had the malfunction persisted, the immediate fallback was manual bag-valve-mask ventilation with one hundred percent oxygen using the bag kept at the bedside. To resolve the high-pressure obstruction, the nurse hyperoxygenates Vince, inserts an inline suction catheter, and clears thick secretions while strictly limiting suction passes to ten seconds. The nurse implements the comprehensive ventilator-associated pneumonia bundle: elevating the head of the bed to thirty-five degrees, providing oral care, initiating daily sedation interruption for a spontaneous breathing trial, and administering subcutaneous heparin and intravenous pantoprazole for prophylaxis. Routine endotracheal saline instillation remains strictly contraindicated due to increased infection risk.
The setup
Respiratory failure lands Vince on the ventilator with an oral endotracheal tube and continuous sedation.
The turn
The high-pressure alarm sounds; he is coughing, secretions rattle, and his SpO₂ dips.
The crisis
Later the low-pressure alarm sounds and the room is quiet — the circuit has come apart at the wye.
The save
Head of bed 30–45 degrees, daily sedation interruption with a spontaneous breathing trial, oral care and DVT and ulcer prophylaxis.
Already a member? Sign in